What the Anion Gap Measures
The anion gap is a computed value used to check acid-base balance and identify various causes of metabolic acidosis. It reflects the difference between measured electrolytes in the blood, especially sodium and chloride, along with bicarbonate. To maintain electrical neutrality, the body, the gap indicates unmeasured ions that can vary during illness or metabolic derangement.
In practical terms, the anion gap is a valuable diagnostic tool when a patient’s lab values indicate an acidotic state. A higher-than-expected result often indicates an accumulation of acids in the bloodstream, while a low or normal result may suggest a different process or a need to review the numbers more carefully.
Most clinicians use an electrolyte panel to obtain the values needed for anion gap interpretation. The common formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. This calculation assists translate raw lab test results into a more meaningful picture of the patient’s internal chemistry.
The anion gap does not confirm a specific disease by itself. Instead, it supports a broader clinical assessment and helps shape the differential diagnosis when the body’s buffering system is under stress. If the result is high, the next step is often to look for a cause of increased acid production, impaired acid clearance, or both.
How Lactate Acidosis Raises the Anion Gap
Lactic acidosis is one of the key causes of a raised anion gap metabolic acidosis. It happens when lactate accumulates faster than the body can remove it, leading to lactate accumulation and a corresponding decrease in bicarbonate. Because lactate is an unmeasured anion, it increases the anion gap as part of the overall acid load.
This process often appears during tissue hypoxia or reduced perfusion, when cells do not receive enough oxygen to meet metabolic demands. Reduced oxygen supply forces tissues to rely more heavily on anaerobic metabolism, which produces lactate as a byproduct. As lactate accumulates, the body moves into a more acidotic state, and the anion gap may increase accordingly.
Sepsis is a common clinical context in which lactic acidosis appears. In critical illness, poor blood flow to organs, inflammatory stress, and impaired metabolism can all lead to rising lactate levels. Because this may progress quickly, an elevated anion gap can be an early signal that something serious is happening, even before the full pattern is obvious on an arterial blood gas.
Lactate acidosis is not the only cause of an increased gap, but it is among the highest-priority to recognize. The relationship between lactate and the anion gap is especially important because the gap can rise even when the initial symptoms are nonspecific. In that setting, the anion gap calculator becomes a useful way to connect lab data with bedside reasoning.
How to Operate an Anion Gap Calculator
An anion gap calculator simplifies the calculation by entering the key lab inputs from the metabolic panel. To get an accurate result, enter the serum sodium, serum chloride, and serum bicarbonate values exactly as reported. The calculator then estimates the gap and helps you compare the result with the expected reference range.
For the calculation to be clinically useful, make sure the values come from the same sample and are interpreted in context. Small changes in sodium, chloride, or bicarbonate can alter the result enough to shift the interpretation from normal to elevated. That is why the calculator is best viewed as a fast analytical step, not a stand-alone answer.
When using the tool, think about what the numbers mean physiologically:
- Serum sodium reflects the main measured cation. Serum chloride and serum bicarbonate are major measured anions in the formula. A lower bicarbonate often signals depletion of buffer during an acid load. An increased gap suggests unmeasured acids may be present.
The calculator helps turn raw lab values into a more interpretable pattern. If the result is elevated, the next step is often to consider lactic acidosis, ketoacidosis, renal dysfunction, or toxin exposure. If the result is not elevated, that does not always end the workup, especially if the patient has symptoms that suggest acid-base disturbance.
Typical, Increased, and Reduced Anion Gap Findings
A expected anion gap often means that the balance between measured cations and anions is inside the expected laboratory reference range. This may be reassuring, but it does not by itself exclude all metabolic problems. A normal result may still occur in initial disease, mixed disorders, or when low albumin masks an increased gap.
A elevated anion gap is more worrisome because it often suggests the presence of additional acids in the blood. In the setting of metabolic acidosis, this pattern suggests a high anion gap metabolic acidosis and should prompt a search for lactate, ketones, renal toxins, and other unmeasured anions. The magnitude of the increase can also help rank the differential diagnosis.
Low anion gap results are uncommon and are often related to lab variation, low albumin, or sometimes other medical conditions. Because albumin is a major unmeasured anion, reduced albumin can make the gap appear lower than it truly is. This is one reason the raw number should never be interpreted in isolation.
The overall context matters as much as the number itself. A patient with suspected critical illness, poor perfusion, or evidence of acidemia may need further evaluation even if the gap is only mildly abnormal. The most useful approach is to combine the anion gap with bicarbonate, pH, lactate, and the overall presentation.
Adjusting the Anion Gap for Serum Albumin
Albumin correction is essential because hypoalbuminemia can mask a clinically significant elevation in the anion gap. Since albumin contributes to the normal unmeasured anions in blood, a low albumin level decreases the expected gap and may make the result look deceptively normal.
That is why the anion gap after correction is often more revealing than the unadjusted value. If serum albumin is below normal, clinicians may raise the number upward to better estimate the true acid burden. This matters especially when evaluating lactic acidosis or other causes of high anion gap metabolic acidosis in hospitalized or critically ill patients.
Consider the correction when the lab pattern does not match the clinical picture. For example, a patient with clear signs of metabolic acidosis and a suspiciously normal gap may still have elevated acids if albumin is low. In that situation, relying on the uncorrected result alone could slow the detection of an important problem.
The key point is that albumin correction improves anion gap interpretation and aligns the calculation more closely with physiology. It helps show an increased anion gap that would otherwise be underestimated because of hypoalbuminemia. In practice, this adjustment is a common step when reviewing lab test results in patients with acute illness.
Other Causes of High Anion Gap Metabolic Acidosis
Even though lactic acidosis is a common cause, it is not the only explanation for an elevated gap. A thorough differential diagnosis should also include ketoacidosis, renal failure, toxic alcohols, and uremia. Each condition can raise the anion gap by adding unmeasured Look at this website acids or hindering normal acid clearance.
Ketoacidosis is frequent in diabetes, starvation, and alcohol-related illness. Ketone bodies gather and consume bicarbonate, producing metabolic acidosis with an increased anion gap. In the right clinical setting, the combination of hyperglycemia, dehydration, and acid-base abnormalities can quickly point toward this diagnosis.
Renal failure can increase the gap because the kidneys are unable to excrete acid effectively. As acid retention worsens, uremia may develop, adding more unmeasured anions into the circulation. This pattern often appears alongside other abnormalities in the electrolyte panel and may be part of a larger picture of systemic illness.
Toxic alcohols are another major cause because they form acidic metabolites after ingestion. These cases can be dangerous and may present with a severe metabolic derangement before the exposure is recognized. Because the presentation can overlap with lactic acidosis, the anion gap helps signal that a serious toxic process may be underway.
When the gap is high, it is useful to think in terms of acid sources rather than a single disease. The calculator gives a clue, but the final diagnosis depends on context, additional testing, and sound clinical reasoning.
Understanding Output in Clinical Context
The anion gap is most useful when assessed alongside an arterial blood gas, pH, and bicarbonate level. These values show whether the patient is acidemic, how intense the disturbance is, and whether compensation is occurring. Taken together, they clarify whether a true metabolic acidosis is present and whether the body is mounting a compensatory response.
As an example, a low bicarbonate level with an elevated anion gap supports high anion gap metabolic acidosis. If the arterial blood gas also shows a low pH, the acid-base disorder is more evident. If pH is near normal, there may be a mixed disorder in which respiratory or metabolic compensation is partly offsetting the abnormality.
The base excess can add another layer of information by estimating the metabolic component of the disturbance. A negative base excess generally supports an acidotic state, while a positive value suggests excess base. This is why clinicians often pair the anion gap with blood gas data rather than relying on a single number.
Clinical symptoms matter as much anion gap clinical significance as the labs. Weakness, rapid breathing, confusion, nausea, abdominal pain, or signs of poor perfusion can strengthen suspicion for a significant acid-base disorder. The combination of symptoms and lab findings helps determine whether the patient is stable or needs urgent intervention.
In short, the anion gap is a starting point for reasoning, not the finish line. It is one piece of the puzzle that becomes much more valuable when combined with serum lactate, blood gas analysis, and the overall clinical picture.
When You Should Seek Urgent Clinical Assessment
An high anion gap can indicate a serious medical emergency, especially when paired with signs of sepsis, shock, or poor perfusion. If the patient has hypotension, declining mental status, or severe respiratory distress, urgent evaluation is needed. These findings may signal rapidly progressive lactic acidosis or another dangerous cause of metabolic acidosis.
Altered mental status is especially concerning because it can reflect worsening acidosis, inadequate oxygen delivery, or organ dysfunction. When this appears alongside an increased anion gap, it may indicate a critical illness that requires prompt assessment and treatment. Delays can allow tissue hypoxia and metabolic derangement to worsen quickly.
Seek urgent care if the anion gap is elevated and the patient appears unstable, especially if there is evidence of infection, dehydration, toxin exposure, or kidney failure. A rising lactate level, severe acidemia on arterial blood gas, or a sharp drop in bicarbonate can all point to a worsening condition that should not be monitored casually.
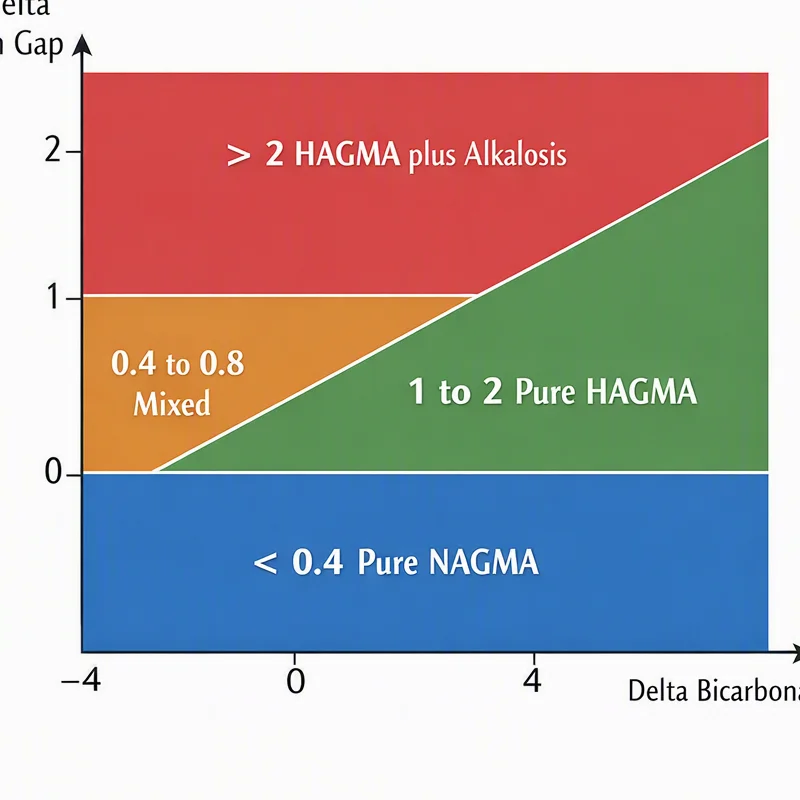
The key message is clear: the anion gap calculator can identify a problem, but the response depends on the clinical setting. When the result fits with shock, sepsis, or serious respiratory and circulatory compromise, prompt evaluation can be lifesaving.
FAQ
What is the anion gap in lactic acidosis?
In lactic acidosis, the anion gap is often high because lactate is an unmeasured anion that collects in the blood. This increase reflects metabolic acidosis caused by acid buildup and decreased bicarbonate. The exact value depends on the lab values and whether albumin is normal or low.
How does an Anion Gap Calculator help identify lactic acidosis?
An Anion Gap Calculator helps identify lactic acidosis by turning serum sodium, serum chloride, and serum bicarbonate into a calculated gap that can suggest an increased anion gap. If the result is high, it raises concern for lactate accumulation and other causes of metabolic acidosis. It is most useful when combined with serum lactate and clinical assessment.
Can a normal anion gap rule out lactic acidosis?
No. A usual anion gap does not fully rule out lactic acidosis, particularly if the increase is beginning, slight, or obscured by hypoalbuminemia. Mixed acid-base disorders can also make the gap appear not as abnormal than expected. If clinical suspicion is high, lactate testing and blood gas analysis may still be needed.
Should the anion gap be corrected for albumin?
Certainly, especially when serum albumin is reduced. Albumin correction helps uncover a corrected anion gap that may more closely reflect the true acid burden. This is important because hypoalbuminemia can make an elevated gap look spuriously normal.
What other conditions can cause a high anion gap besides lactic acidosis?
Other common causes include ketoacidosis, renal failure, toxic alcohols, and uremia. These conditions can all produce a high anion gap metabolic acidosis through distinct mechanisms. The correct diagnosis depends on the full lab pattern, symptoms, and clinical context.