What the Anion Gap Measures
The anion gap is a valuable diagnostic marker that helps healthcare providers and patients interpret lab results as part of a larger assessment of pH balance. An anion gap calculator determines the gap between measured serum electrolytes in the blood chemistry panel, which reflects electrolyte balance and can point toward specific acid-base disorders.
In practical terms, the anion gap compares the primary positively charged and negatively charged ions reported on a routine electrolyte panel. The most important values are sodium, chloride, and bicarbonate. Because not all ions are directly measured, the anion gap helps reveal whether there are other unmeasured acids in the bloodstream.
This makes the anion gap especially important in metabolic acidosis evaluation. A high result can suggest extra acid accumulation, while a normal result may reflect a different pattern of acid loss or compensation. The calculation does not serve alone, but it gives important context for clinical interpretation of the anion gap lab result.
Think of it as part of a larger serum electrolytes review. It is not a standalone diagnosis, but it can support the next steps in patient assessment and help rule out causes of abnormal blood chemistry.
How to Calculate the Anion Gap
The typical anion gap formula uses serum sodium, serum chloride, and serum bicarbonate. The most widely used version is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation calculates the difference between measured cations and anions. If you use an anion gap calculator, you simply enter the laboratory values from the basic metabolic panel or another electrolyte panel, and the tool computes the result immediately.
Here is a straightforward example of how to calculate anion gap from lab results:
- Serum sodium: 140 Serum chloride: 102 Serum bicarbonate: 24
Using the formula: 140 - (102 + 24) = 14. That value might fall within a normal reference range, depending on the lab.
Some clinicians also use variants that include potassium, but the sodium-based version is the preferred for routine clinical interpretation. No matter the version, the goal is the same: to detect patterns that may suggest metabolic acidosis or other shifts in acid-base balance.
Normal Anion Gap Range and Reference Values
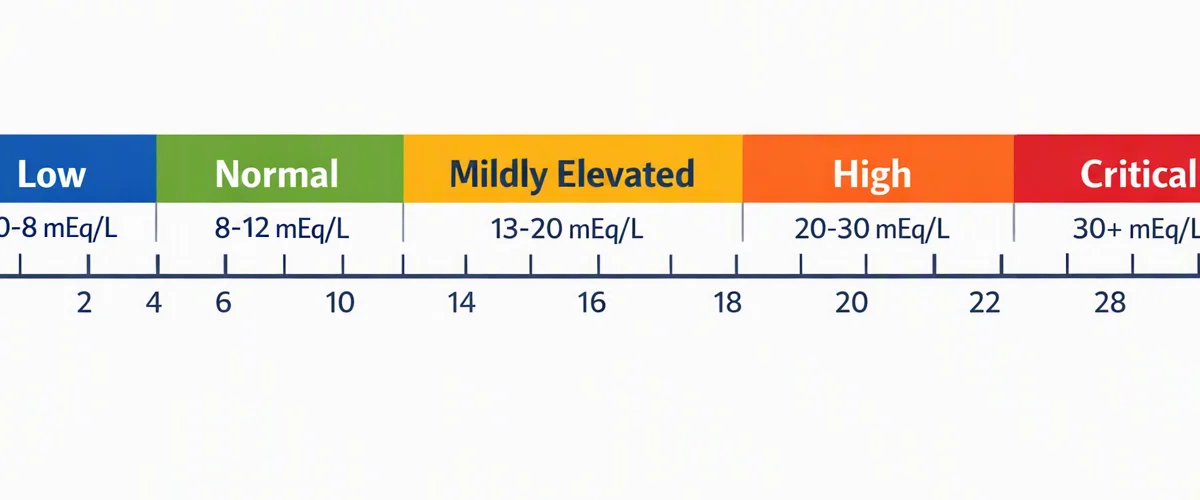
The normal range for anion gap depends on the laboratory’s method and reporting system. That is why the exact lab reference range should always be checked alongside the result. Different analyzers, assays, and calculation methods can create lab variability.
In many settings, the typical range is narrow, but the acceptable value may differ based on whether potassium is included and whether the result is corrected for albumin. Because of this, a result that looks “high” in one lab may be considered normal in another. Always use the specific lab reference values linked to that report.
Albumin also matters because it is one of the major unmeasured anions in blood. When serum albumin is low, the measured anion gap can appear falsely unchanged or low, even when an acid-base problem exists. That is why interpreting the number without considering albumin can lead to missed how to interpret AG abnormalities.
In short, the “normal” value is not just a fixed number. It is a situational result that must be interpreted with the lab’s stated reference range, the patient’s overall status, and other laboratory findings.
Corrected Anion Gap and Albumin Correction
Hypoalbuminemia is among the most important reasons to adjust the anion gap. Since albumin contributes substantially to the unmeasured anions in blood, a low albumin level can decrease the apparent gap. That is why albumin adjustment becomes important.
The adjusted anion gap helps adjust for reduced blood albumin. This adjustment enhances the accuracy of the result when evaluating possible metabolic acidosis. If the gap is not adjusted, a clinically important elevation may be missed.
A common approach is to add a correction factor when albumin is below normal. While formulas may show minor variation by institution, the goal is the same: estimate what the anion gap would be if albumin were normal. This makes the result more dependable for patient review and medical interpretation.
For example, a patient with low albumin may have an anion gap that appears normal, but after albumin correction, the value may suggest hidden elevated anion gap acidosis. In real-world practice, this is why albumin should be reviewed whenever the anion gap is used to read laboratory results.
When using an Anion Gap Calculator, look for a version that includes albumin adjustment or allows you to manually apply the correction. This is especially useful in complex cases and in patients with chronic illness, malnutrition, or inflammation.
Increased Anion Gap Compared with Expected Anion Gap Acidosis
A key point of the anion gap is separating elevated anion gap from typical anion gap acid-base acidosis. Each are patterns of metabolic acidosis, but they reflect different mechanisms.
In increased anion gap acidosis, acid anions accumulate in the blood. Typical causes include lactic acidosis, ketoacidosis, and renal failure. These conditions raise acid production or impair acid clearance, which raises the gap.
In typical anion gap acidosis, the bicarbonate level decreases but the gap remains within the usual range because chloride increases to maintain electrical balance. This pattern is often called chloride-associated acidosis. It is a separate acid-base pattern from classic high gap states.
Understanding the difference helps direct the next steps in metabolic acidosis evaluation. A high gap suggests looking for acid accumulation or toxin exposure. A normal gap suggests considering bicarbonate loss, renal tubular issues, or other causes of acid-base disturbance.
The anion gap therefore works as a diagnostic marker that narrows the differential. It does not replace the full assessment, but it helps connect the numbers to the likely physiology.
Frequent Causes of Abnormal Anion Gap Results
Altered anion gap results can reflect many disorders, and the most useful approach is to assess the patient context along with the laboratory findings. Frequent causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and uremia.
Lactate increases when tissues are under stress and oxygen delivery or utilization is impaired. This can happen in severe illness, shock states, or other conditions that increase anaerobic metabolism. Elevated lactate is a typical cause of high gap acidosis.
Ketoacidosis occurs when ketone production builds, often in diabetes, prolonged fasting, or alcohol-related metabolic states. It can create a marked anion gap increase and should be considered when blood glucose or ketones are abnormal.
Renal failure can reduce the kidneys’ ability to clear acids, leading to uremia and accumulation of unmeasured anions. This is another classic cause of high gap abnormalities.
Other causes involve toxins and drug exposures. Salicylates can produce mixed acid-base findings and may elevate the gap. Other toxins can also contribute to an abnormal result, so history and medication review are essential parts of the workup.
Because several conditions can overlap, the anion gap should be interpreted alongside symptoms, medication use, and the broader pattern of laboratory data.
How to Interpret Outcomes With Other Lab Tests
The anion gap becomes significantly more useful when reviewed with other tests. A basic metabolic panel supplies the core electrolyte values, but additional studies often explain the cause of the abnormality and direct treatment decisions.
An arterial blood gas can show pH, partial pressure of carbon dioxide, and bicarbonate in greater detail, helping define the type and severity of the acid-base disorder. A venous blood gas can also be useful in many settings, especially when repeated monitoring is needed and arterial sampling is not necessary.
The osmolar gap is another key companion test when toxins or unusual ingestions are possible. A high osmolar gap may support concern for certain toxic alcohol exposures, while the anion gap may show concurrent metabolic changes.
When used together, these tests support a structured clinical interpretation of acid-base balance. The anion gap helps identify unmeasured acids, the blood gas shows the physiologic effect, and the osmolar gap can point toward specific toxic causes. This combination improves the ability to rule out causes and determine whether the problem is a primary metabolic issue, a mixed disorder, or a compensatory response.
In real practice, the best results come from using the anion gap formula with the rest of the lab picture rather than viewing one number in isolation.
When to Get Medical Review
Certain anion gap findings need prompt review, especially when the result is paired with concerning symptoms or other abnormal labs. A substantially raised or unexpected value may represent a critical problem that needs immediate attention.
Critical values should always be handled according to local lab policy and the patient’s condition. Even if the number is not formally flagged, a significant change from prior results can matter. Trend interpretation is often more valuable than a single isolated number.
Seek urgent assessment when the abnormal result occurs with symptoms such as severe weakness, confusion, rapid breathing, vomiting, chest discomfort, or reduced consciousness. These findings may point to significant metabolic acidosis, toxic exposure, severe lactic acidosis, or another acute problem.
It is also important to use clinical judgment. The same anion gap value can mean different things in different patients depending on the reference range, albumin level, kidney function, and other laboratory findings. A number that seems mild in one case may be clinically important in another.
An anion gap calculator assists with decision-making, but it does not replace medical review. If the result is abnormal and the person is unwell, immediate evaluation is appropriate.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to work out anion gap values from lab results and support interpretation of lab results in the setting of acid-base balance. It is especially helpful in metabolic acidosis evaluation, where it can suggest whether the problem is likely to be a high anion gap state or a normal anion gap pattern. It also supports review of the anion gap lab result alongside the rest of the electrolyte panel.
How do you determine the anion gap from lab results?
Apply the anion gap formula: serum sodium less the sum of the sum of serum chloride and serum bicarbonate. In other words, anion gap = serum sodium - (serum chloride + serum bicarbonate). It uses values from the basic metabolic panel or another electrolyte panel and is the typical way to work out the result.
What is a normal anion gap range?
The normal range depends on the laboratory’s technique and reported lab reference range. Because of lab variability, always check the result with the specific report rather than relying on a single universal number. Albumin and whether the value is corrected for albumin can also affect interpretation, so the best answer always comes from the exact laboratory context.
Why do you correct the anion gap for albumin?
You modify the anion gap for albumin because hypoalbuminemia can make the gap look artificially low or normal. Since serum albumin contributes to unmeasured anions, albumin correction improves accuracy and may reveal hidden acid accumulation. A corrected anion gap is especially useful when trying to identify occult high gap acidosis.
What does a high anion gap mean?
A high anion gap usually means there are extra unmeasured acids in the blood, which often points to metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and uremia. It can also be associated with salicylates or other toxins. The result should be interpreted together with symptoms, blood gas testing, and the rest of the laboratory findings for accurate clinical interpretation.