What Is the Anion Gap?
The anion gap is a figure calculated from a standard blood test that helps clinicians check the status of electrolytes in the body. It is taken from a routine serum chemistry or electrolyte panel and is used to support evaluation of acid-base balance. Although the term sounds highly specialized, the idea is straightforward: the result reflects the difference between measured positively charged ions and measured negatively charged ions in the blood.
This difference matters because it can indicate the presence of unmeasured anions or unmeasured cations that are not obvious from a basic panel alone. In clinical practice, the anion gap serves as a diagnostic tool and a quick way to guide result analysis when an acid-base disorder or other metabolic disturbance is suspected.
An anion gap calculator makes this process simpler by using common lab values to calculate the result in seconds. But the number only becomes useful when you understand what it means in medical context. A normal result may be reassuring, while an abnormal one can point toward issues such as metabolic acidosis, low albumin, or other conditions that call for further review.
Anion Gap Calculation and Equation
The common anion gap equation takes recorded values from the blood, specifically serum sodium, serum chloride, and serum bicarbonate. The standard anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians use a different version that includes potassium, but today’s calculators use the more basic version above because it is widely accepted and handy for standard interpretation.
Here is the basic logic behind the equation:
- Sodium represents the primary measured cation. Chloride and bicarbonate represent the main measured anions. The gap reflects the balance between measured positive and negative charges.
When you calculate the anion gap, you are not finding a gap in the literal sense. You are approximating the amount of charge carried by unmeasured substances in the blood. That is why the anion gap equation is so valuable for identifying an acid-base disorder and for identifying patterns in a serum chemistry result.
A above-normal result suggests additional unmeasured acids or other compounds, while a reduced result can suggest a loss of negatively charged proteins or a measurement problem. Because of that, correct use of the anion gap formula depends on the complete lab picture, not just one individual number.
How the Anion Gap Calculator Works
An anion gap calculator is built to streamline the math and minimize manual errors. You enter the input values from the electrolyte panel, and the calculator performs the calculation steps automatically. In Hop over to this website most cases, you supply sodium, chloride, and bicarbonate values, then the tool gives the anion gap along with a reference range or interpretation note.
The process usually works like this:
- Provide the sodium value from the blood test. Enter the chloride value. Provide the bicarbonate value. Check the calculated result and assess it with the reference range.
Many users rely on an online calculator because it supports quick pattern recognition during result analysis. It is especially useful when reviewing an electrolyte panel in a busy clinical setting or when trying to understand whether a lab pattern suggests a broader metabolic issue.
Even though the calculator is simple, the numbers still need context. A value that falls within the reference range may still be abnormal if albumin is low or if another condition is changing the baseline. That is why the calculator is best viewed as a first step in interpretation, not the final answer.
In practical use, the calculator helps identify whether the result fits a typical normal anion gap pattern or whether further review is needed. It can also support decision-making when the goal is to understand possible causes of metabolic acidosis or other acid-base changes.
Expected Anion Gap Range and What Changes It
The reference range for the anion gap can vary by laboratory because of changes in testing methods, analyzer calibration, and reporting practices. This is where lab variation is important. A result that is deemed normal in one setting may be somewhat different in another, so the lab’s own reference range should take priority.
Several factors can alter the number:
- Albumin: As albumin is a primary unmeasured anion, lower levels can decrease the measured gap. Lactate: Elevated lactate can raise the gap because it adds unmeasured anions. Lab variation: Different instruments and methods may produce slightly different values.
Albumin is especially significant because it is one of the primary contributors to the anion gap. When albumin is low, the normal anion gap may appear falsely reassuring. In those cases, an albumin correction or albumin adjustment may be needed to estimate a more accurate corrected anion gap.
That matters because a patient can have a meaningful acid-base problem even if the raw number seems normal. For that reason, interpreting the value without checking albumin can lead to missed abnormalities. Similarly, elevated lactate can shift the result upward even before other abnormalities are obvious.
High Anion Gap: Common Causes
A elevated anion gap usually suggests the presence of unaccounted-for acids in the blood. The most common clinical concern is metabolic acidosis, where acid builds up or bicarbonate is depleted in a way that increases the calculated gap.
These causes include:
- Lactic acidosis, often associated with poor tissue oxygen delivery, severe illness, or impaired lactate clearance. Ketone-related acidosis, which can occur when ketone bodies accumulate during insulin deficiency, starvation, or other metabolic stress. Kidney failure, where reduced acid excretion causes acids to persist. Poisoning, including certain substances that generate unmeasured acids or interfere with normal metabolism.
This matters because they suggest different treatment pathways. For example, lactate acidosis suggests a search for tissue hypoperfusion or severe infection, while ketoacidosis indicates abnormal fat metabolism and requires a different management approach. Impaired kidney function may result in acid retention over time, and poisoning can cause a dangerous metabolic picture that needs urgent assessment.
A high value is not a diagnosis by itself. It is a clue that should be considered alongside symptoms, history, and the rest of the blood test results. In many cases, it prompts more testing to identify the underlying cause and to determine how severe the metabolic disturbance is.
Reduced Anion Gap: Typical Causes
A low anion gap is not as common than a high one, but it can still be medically significant. One of the leading explanations is hypoalbuminemia, because albumin is a negatively charged protein that contributes to the normal gap. When albumin falls, the calculated value can fall with it.
Other common causes include:
- Paraproteinemia, where abnormal proteins in the blood alter the balance of measured and unmeasured ions. Lab error, including specimen issues or measurement problems that distort the reported electrolytes.
Hypoalbuminemia is particularly important because it can hide a serious condition if the result is interpreted without an albumin correction. In some patients, the corrected value may reveal a more significant disorder than the unadjusted number suggests. This is why a corrected anion gap can be more revealing than the raw calculation alone.
Paraproteinemia should be considered when abnormal proteins are present, particularly if other findings do not match the apparent result. And because lab error is always possible, an unexpected low result should be reviewed carefully before drawing conclusions. Repeating the test or checking the full electrolyte panel may help confirm whether the number is real.
Clinical Use of the Anion Gap in Acid-Base Disorders
The anion gap is particularly helpful when used as part of a more comprehensive assessment of acid-base disorders. It helps distinguish different types of metabolic acidosis and supports the work of pattern recognition when reviewing a blood test, electrolyte panel, and serum chemistry results together.
In practice, the anion gap helps address questions such as:
- Is the acidosis related to accumulation of unmeasured acids? Does the pattern suggest bicarbonate loss instead? Is the gap elevated enough to justify looking for lactate, ketones, toxins, or renal dysfunction?
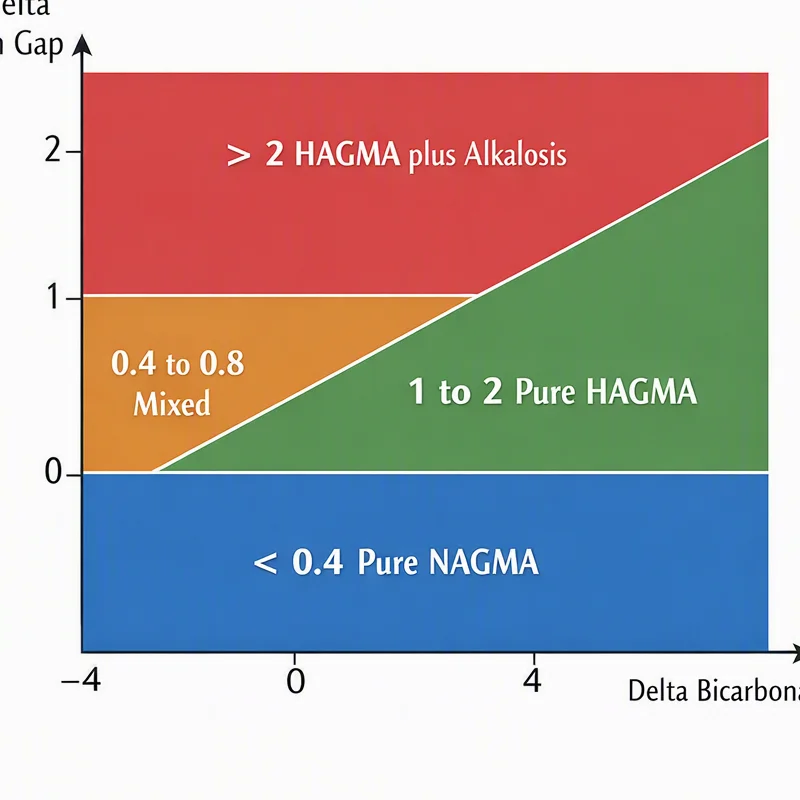
Another important concept is the delta gap, which contrasts the change in anion gap with the change in bicarbonate. This can help identify mixed disorders, where more than one metabolic process is happening at the same time. That is useful because a patient may have a high anion gap acidosis and another acid-base problem simultaneously.
A blood gas is often interpreted alongside the anion gap to give a fuller picture of acid-base status. The blood gas shows pH and respiratory compensation, while the anion gap helps pinpoint the underlying metabolic component. Together, they improve clinical significance and help with cause assessment.
This is why the anion gap remains a practical diagnostic tool: it turns a simple lab calculation into a meaningful guide for evaluating complex metabolic disturbances.
Interpreting Outputs Safely
Sound clinical interpretation needs more than just looking at one number. The anion gap should be reviewed in the light of clinical symptoms, the full electrolyte panel, medication history, kidney function, and any other signs of illness. A result that seems abnormal may be explained by timing, fluid status, protein changes, or measurement differences.
Careful interpretation involves a few steps:
- Verify the values used in the calculation. Confirm whether the lab’s reference range differs from other sources. Review albumin and consider albumin adjustment if needed. Look for signs of electrolyte imbalance or metabolic acidosis. Find clinical clues that back up or oppose a suspected cause.
If the result suggests a significant problem, a medical evaluation is important. This is especially true when symptoms such as confusion, rapid breathing, dehydration, vomiting, or severe weakness are present. The anion gap is helpful, but it does not replace a full assessment of the person and the illness.
In other words, the number should inform the next step, not serve as the final conclusion. Combining the calculator result with clinical context improves accuracy and reduces the risk of missing an important problem.
Frequently Asked Questions
What is the anion gap calculator used for?
The anion gap calculator is used to calculate the anion gap from common blood test values, usually sodium, chloride, and bicarbonate. It helps with interpretation of acid-base balance and can point toward a metabolic disturbance such as metabolic acidosis.
How do you calculate the anion gap?
The most common anion gap equation is: sodium minus the sum of chloride and bicarbonate. In short, the anion gap formula is sodium − (chloride + bicarbonate). Some versions may include potassium, but the simpler formula is widely used.
What’s a typical anion gap value?
The reference range is influenced by the laboratory and analysis used, so the normal range on the report should be checked first. A result in the expected range generally suggests no major build-up of hidden acids, but low albumin and measurement differences can change the number.
Why does there be a high anion gap?
A elevated anion gap is often due to metabolic acidosis from issues like lactate buildup, ketone buildup, renal failure, or poisoning. These issues add unmeasured acids to the blood and increase the calculated result.
Can a low anion gap suggest a medical problem?
Yes. A reduced anion gap can be associated with reduced albumin, paraproteinemia, or measurement error. It may also reflect other changes in electrolytes or proteins, so it should be reviewed in clinical context rather than dismissed.