What Is an Anion Gap?
The anion gap is a computed value used to assess an electrolyte panel and recognize issues in acid-base balance. It compares the key measured serum electrolytes to estimate whether there are extra unseen acids or other charged particles in the blood. In simple terms, an anion gap calculator gives a rapid snapshot of whether the chemistry pattern suggests a hidden metabolic issue.
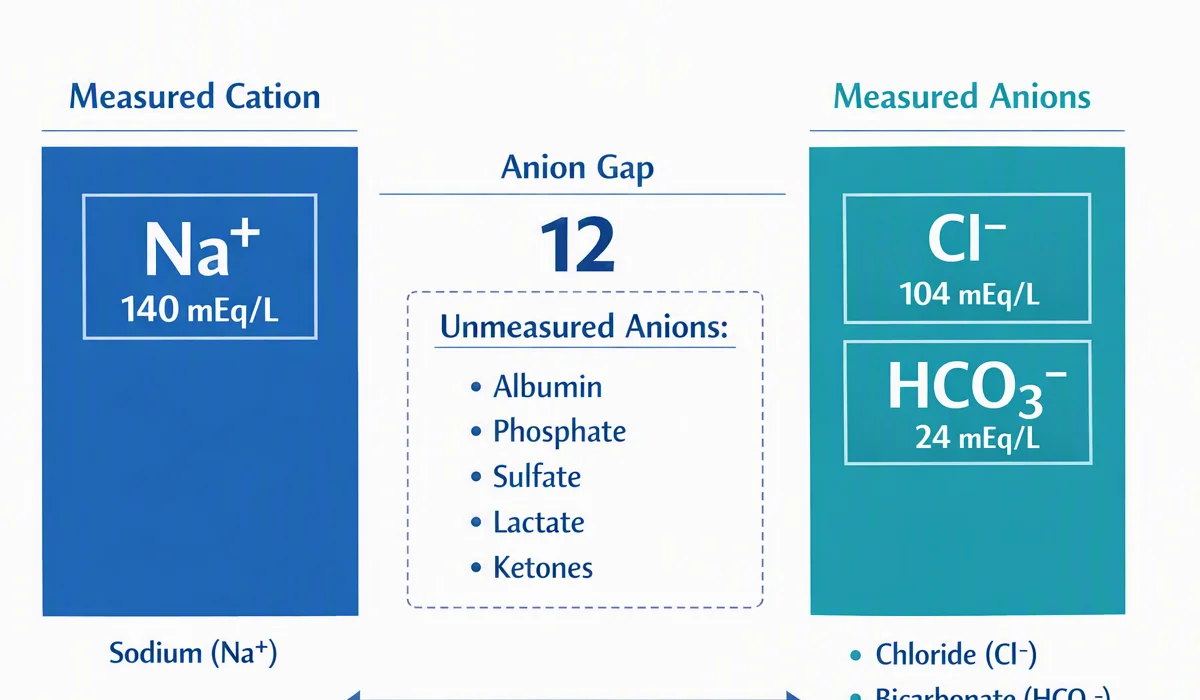
Because the bloodstream must remain electrically balanced, the measured cations and anions do not perfectly match. The difference is the anion gap. This makes it a valuable diagnostic clue in evaluating an acid-base disorder, especially when metabolic acidosis is suspected. Clinicians often use the result as a screening tool before choosing whether more testing is needed.
The concept is most useful when paired with the rest of the serum chemistry picture. Sodium, chloride, and bicarbonate are the primary measured values, but the result can also reflect the presence of unmeasured anions such as organic acids or albumin-related charges. That is why the anion gap is not just a number; it is part of a larger clinical interpretation process.
How the Anion Gap Calculator Works
An anion gap calculator relies on a simple formula based on sodium, chloride, and bicarbonate. The standard anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This calculation measures the difference between the key measured positive and negatively charged ions in the blood. Sodium is the largest measured cation in standard lab testing, while chloride and bicarbonate are the principal measured anions. The link among these values may indicate whether the body has built up acids that are not directly measured on a routine panel.
The calculator does not identify a disease by itself. Instead, it provides interpretation that assists in narrowing the differential diagnosis. For example, a elevated result suggests added acid burden, while a low result may point toward reduced protein charge, measurement issues, or unusual electrolyte patterns. The strength of the tool is its clinical utility: it instantly connects the numbers to likely physiology.
Some versions of the calculation include potassium, but many routine clinical approaches use sodium, chloride, and bicarbonate alone. For most users reviewing an electrolyte panel, the simplified equation is the most familiar and simplest to apply.
How to Determine Anion Gap From a Basic Metabolic Panel
A metabolic panel usually includes the data needed for the determination: serum sodium, serum chloride, and serum bicarbonate. After those numbers are available, the calculation is straightforward and can be done by hand or with an online tool.
To work out the anion gap from a basic metabolic panel, use these steps:
- Locate the serum sodium value. Identify the serum chloride value. Find the serum bicarbonate value. Combine chloride and bicarbonate together. Subtract that sum from sodium.
The result is the anion gap. Because the panel is standardized serum chemistry, this is a fast way to obtain a calculation that assists in evaluation of a possible metabolic disturbance.
As an example, if sodium is 140, chloride is 104, and bicarbonate is 24, then 104 + 24 = 128, and 140 - 128 = 12. That value may be within the expected reference range depending on the laboratory method used. The important point is not only the number itself, but how it fits with the rest of the lab values and the patient’s condition.
Typical Anion Gap Range & Reference Intervals
The reference range for anion gap varies by the laboratory and its particular testing method. Several analyzers and reporting systems can produce marginally different reference interval values. That means the same result may be considered normal in one lab and borderline in another.
One major factor is albumin, a negatively charged plasma protein that influences the apparent gap. Because albumin carries much of the unmeasured negative charge in blood, lower albumin can lower the measured anion gap. This is one reason the result should always be read in context rather than treated as a standalone diagnosis.
Laboratory variation matters as well. The technique used for electrolyte measurement can affect the reported value, so the site-specific reference interval should be used whenever possible. In practice, clinicians focus on whether the number is clearly increased, low, or unexpectedly normal given the acid-base picture.
In some settings, a slightly higher or lower result may still be acceptable if the overall clinical picture does not suggest a significant disorder. That is why the anion gap is best viewed as part of broader clinical interpretation rather than as an isolated cutoff.
High Anion Gap vs Typical Anion Gap Metabolic Acidosis
A metabolic acid buildup stands as one of the main reasons to check an anion gap. A increased anion gap usually indicates that more acids are found in the blood, raising the number of unmeasured anions. A typical anion gap acidotic state, by contrast, implies that bicarbonate has been lost and replaced by chloride, so the overall gap holds about the same value.
In a increased anion gap state, acid is added to the body at a greater rate than it can be removed or buffered. In a typical anion gap pattern, the main problem is often a move in chloride and bicarbonate rather than an increase of new acids. That distinction helps shape the differential diagnosis and determine the next steps in evaluation.
Understanding the relationship between the gap and pH balance also helps explain why the result matters. The body uses buffering systems to maintain stable pH. When those systems are exceeded, the chemistry panel may show a higher gap or a normal gap pattern that still reflects serious disease.
A low anion gap is rarer but can occur when albumin is reduced, when unmeasured cations are present, or when there is measurement artifact. It should not be ignored if it is unexpected, because it may be a clue to a distinct issue affecting the serum chemistry pattern.

Frequent Causes of an Elevated Anion Gap
An elevated result often points to the build-up of acids or other charged substances that are not directly measured in the panel. The most common causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
Lactic acidosis occurs when lactate builds up, often because tissues are not receiving enough oxygen or because metabolism is otherwise stressed. This creates extra acid and raises the anion gap. Ketoacidosis, including diabetic ketoacidosis and other ketosis states, can also elevate organic acids in the blood and widen the gap.
Renal failure can lead to acid retention because the kidneys are no longer clearing acids effectively. As acid accumulates, the anion https://anion-gap-help585.inkharbory.com/posts/what-toxins-can-cause-a-high-anion-gap gap rises. Toxin ingestion is another important category because certain ingested substances generate acids or interfere with metabolism, leading to a significant gap elevation.
Other causes can also be present, but these major categories are central to interpretation. An elevated result is not a final diagnosis; it is a cue to review symptoms, history, and additional labs. That is why the anion gap is best used as a diagnostic clue rather than a standalone answer.
In What Way Low Albumin Affects the Anion Gap
Albumin strongly changes the anion gap because it contributes negative charge to the plasma. If albumin is low, the measured gap can look lower than expected despite the fact that the underlying acid-base status is abnormal. That is why hypoalbuminemia can conceal a clinically important problem.
A anion gap correction accounts for low albumin to more reliably reflect the true acid-base state. The need for correction arises from albumin’s role in protein electrical charge and the distribution of charged particles in plasma. Without this adjustment, a patient with significant metabolic disturbance may seem to have a less impressive result than they actually do.
The exact correction method can change, but the overall idea is the same: lower albumin means the uncorrected number may underestimate the true gap. A corrected value can therefore strengthen clinical interpretation, especially when symptoms or other lab findings suggest acidosis.
Because albumin is so significant, any abnormal result should be reviewed alongside the protein level if available. This is particularly relevant when the anion gap appears normal despite signs of acidic metabolic disturbance.
Stepwise Sample Applying an electrolyte test panel
This is an example calculation based on common electrolyte values taken from an electrolyte panel:
- Serum sodium: 138 Serum chloride: 100 Serum bicarbonate: 16
Step 1: Sum the chloride and the bicarbonate. 100 + 16 = 116.
Next: Subtract the total from the sodium value. 138 - 116 = 22.
The anion gap is 22.
This result is elevated in many reference systems and suggests a likely high anion gap pattern. The next question is not simply whether the number is high, but what the clinical context shows. If the patient has diabetes, poor intake, or vomiting, ketoacidosis may be a concern. If there is shock, infection, or low oxygen delivery, lactic acidosis becomes more likely. If kidney function is poor, renal failure may explain the finding.
Now, look at the same patient with an albumin of 2.5. In that setting, the uncorrected value might miss the degree of abnormality. A adjusted anion gap can offer a more accurate interpretation and better reflect the true metabolic disturbance. This is exactly why the calculator is most useful when paired with the full lab picture rather than relied on in isolation.
Drawbacks of the Anion Gap Calculator
As with any screening method, an anion gap calculator is limited. One major issue is measurement error. Small differences in how sodium, chloride, and bicarbonate are measured can alter the final number, especially when the result is near the edge of the reference range.
Laboratory methods also count. Various analysis technologies and electrolyte measurement techniques can produce varying results, which is why the lab’s reference range should always be used. A value that seems out of range in one environment may be acceptable in another.
Another challenge is the role of unmeasured cations. Compounds like lithium or other positively charged ions can alter the calculation and reduce the apparent gap. Moreover, abnormal protein levels, changes in plasma proteins, and unusual clinical situations can create patterns that do not fit a simple formula.
In the end, the calculator cannot replace clinical interpretation. Symptoms, vital signs, blood gas results, kidney function, and glucose or lactate levels may be needed to understand what the result really means. This measure is helpful, but it is only one piece of the assessment.
When to Seek Urgent Medical Evaluation
Particular anion gap abnormalities suggest a potentially dangerous illness that requires prompt attention. If there are signs of severe acidosis, the situation may become urgent quickly. Symptoms can include rapid breathing, confusion, marked weakness, severe nausea, vomiting, abdominal pain, or decreased responsiveness.
Highly abnormal results or other critical values on the chemistry panel may signal a serious metabolic problem. When the gap is high and the patient is ill, immediate evaluation may be necessary to determine whether there is lactic acidosis, ketoacidosis, toxin exposure, or kidney failure.
Because the anion gap is a diagnostic clue, not a diagnosis, symptoms and the overall picture should guide the response. If there is concern for severe illness, emergency care is appropriate. Delay can be dangerous when the body is struggling to maintain acid-base balance.
Frequently Asked Questions
What is the anion gap on an electrolyte panel?
The anion gap is a calculated value from an electrolyte panel that helps assess acid-base balance. It estimates the difference between measured cations and measured anions, mainly using sodium, chloride, and bicarbonate. It is often used as a screening tool for metabolic problems.
How can you calculate anion gap using sodium, chloride, and bicarbonate?
Apply the anion gap formula: sodium less the total of chloride and bicarbonate. In other words, Anion gap = serum sodium - (serum chloride + serum bicarbonate). This is the standard calculation used by an anion gap calculator.
What does an elevated anion gap mean?
A increased anion gap usually means that unmeasured acids are present, which is a common pattern in metabolic acid buildup. Typical causes include lactic acid buildup, ketone buildup, kidney failure, and toxin ingestion. It is a clue that further assessment is needed.
How does low albumin affect the anion gap?
Albumin carries negative charge, so reduced albumin can lower the measured anion gap. In that case, a corrected anion gap may better reflect the real acid-base condition. Low albumin can hide an important elevation if the result is not compensated.
Can a normal anion gap still be abnormal in acid-base disorders?
Yes. A normal anion gap does not rule out an disorder of acid-base balance. Some forms of metabolic acidosis keep the gap normal because bicarbonate loss is balanced by chloride gain. That is why the result must be interpreted with the rest of the laboratory values and the full clinical picture.