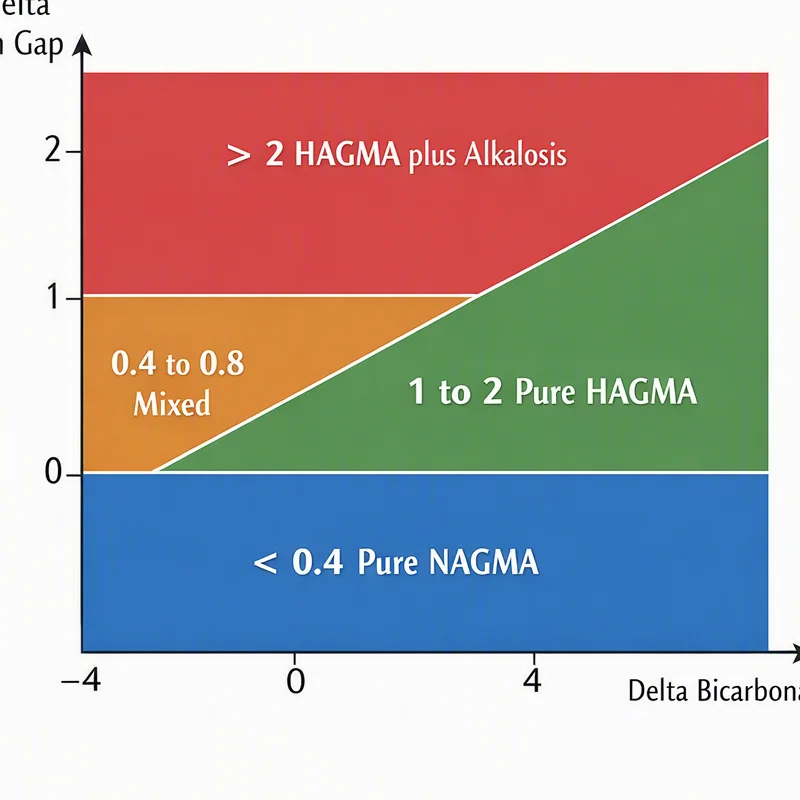
How the Anion Gap Assesses
The anion gap is a straightforward way to estimate the relationship between measured positive and negatively charged particles in the blood. It is most often used as a diagnostic tool for detecting an electrolyte imbalance and helping evaluate metabolic acidosis. By comparing common electrolytes such as sodium, chloride, and bicarbonate, clinicians can infer whether there are extra unmeasured anions present in the bloodstream.
This matters because the body depends on tight acid-base balance to keep cells functioning normally. When that balance shifts, the change may indicate an underlying acid-base disorder, a metabolic disturbance, or a problem with kidney function. An anion gap result does not confirm a condition by itself, but it can direct the next step in evaluation.
The anion gap is derived from serum electrolytes and other values reported on a blood chemistry or electrolyte panel. Because it is based on routine blood tests, it is widely used in screening. In practice, the number helps show whether the blood contains higher levels of acids, such as organic acids, or whether a low result is due to reduced proteins like albumin.
How to Work with an Anion Gap Calculator
An anion gap calculator is a simple calculation aid that relies on values from a routine chemistry panel. The usual inputs are sodium, chloride, and bicarbonate, and some versions also include potassium. The calculator then uses a formula to estimate the gap and compare it with a normal reference range.
To use the calculator correctly, input the measured lab values exactly as reported. Small changes in one input can shift the result, especially when the overall anion concentration is close to the normal range. Since the output is only as accurate as the data entered, it is crucial to confirm the numbers from the serum chemistry report and not from memory.
A practical workflow is:
- Obtain the values from the electrolyte panel. Check whether the calculator uses the standard or potassium-included method. Add sodium, chloride, bicarbonate, and potassium if needed. Interpret the result in the context of the patient’s symptoms and other blood tests.
The calculator is a supportive and evaluation aid, not a replacement for clinical interpretation. A single number should always be assessed alongside the full clinical picture, including medications, hydration status, and signs of acid-base disorders.
When Potassium Is Counted in the Formula
Potassium is occasionally included because it is also a cation in the blood and can be counted in the equilibrium between measured ions. The standard or traditional anion gap calculation usually omits potassium because its concentration is comparatively small compared with sodium. However, a modified anion gap adds potassium and can give a slightly higher result.
The difference is important when comparing calculators or reading older literature. If potassium is included, the calculated gap will usually increase by a few units, but the clinical meaning may stay similar. That is why a result must always be interpreted based on which formula was used.
There are situations where the potassium-included method may be preferred, especially in theoretical discussions of acid-base balance or when a system is designed to account for all major measured cations. Even then, most bedside and routine references still rely on the traditional anion gap, so agreement matters more than the specific method itself.
In simple terms, the potassium-included version is a modified anion gap approach that includes one more measured electrolyte to the calculation. The result can be useful, but it should not be mixed with standard reference values from a calculator that excludes potassium.
Anion Gap Equation and Stepwise Calculation
The calculation formula depends on whether potassium is included. The usual traditional form is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula becomes:
Modified anion gap = sodium + potassium - (chloride + bicarbonate)
These equations use serum electrolytes from a standard blood chemistry panel. To interpret it fully, it can also help to review albumin, since albumin is a major unmeasured anion and a low level can reduce the apparent gap.
Here is a step-by-step example using the potassium-included method:
- First take the measured sodium. Then add potassium if the calculator uses the modified method. Add together chloride and bicarbonate. Subtract the chloride-bicarbonate total from the sodium-plus-potassium total.
Example: if sodium is 140, potassium is 4, chloride is 102, and bicarbonate is 24, then the modified anion gap is 140 + 4 - (102 + 24) = 18.
The calculated value should then be measured against the correct baseline value for the specific formula used. If albumin is low, a correction may be needed because the raw number can underestimate the severity of a metabolic problem. For that reason the calculator is only the starting point, not the final answer.
Typical Range and How High or Low Values Are Interpreted
The normal range varies with the testing method and on whether potassium is included. For the classic anion gap, many expected values lie within a narrow band, while the potassium-included version is typically a slightly higher. A calculator should present the method clearly so the result is understood against the correct reference range.
A increased anion gap often indicates extra acids or unmeasured anions in the blood. This can happen in several serious conditions and often points toward metabolic acid buildup. sepsis metabolic acidosis AG A low anion gap is less common, but when present it can indicate low albumin, analytical issues, or other unusual protein changes.
Understanding whether the value is somewhat abnormal or clearly outside the expected range is part of good medical interpretation. A small shift may reflect minor variation in lab test results, while a more pronounced abnormality can signal a true acid-base imbalance.
The most useful approach is to compare the number with the patient’s overall condition, the rest of the electrolyte results, and related findings such as kidney markers and acid levels. In other words, the calculator gives a number, but the clinician assigns meaning to that number.
Common Causes of an Elevated Anion Gap
A high anion gap usually means there are more undetected anions in the blood. A common cause is lactic acidosis, which occurs when the body generates or removes lactate poorly. This often reflects tissue hypoxia, severe illness, or an additional process that increases acid load.
Ketoacidosis is another major cause. In this setting, ketone bodies collect and elevate the gap. It may occur with diabetes, starvation, or prolonged alcohol use. Because ketones are organic acids, the anion gap can go up as bicarbonate is consumed during buffering.
Renal failure can also cause the gap to rise because the kidneys are not as able to excrete acids. Reduced renal function leads to retention of acid and other metabolic byproducts, which can contribute to acidosis. This renders the anion gap a helpful clue in evaluating kidney-related metabolic disturbance.
Other key causes include toxic alcohols, which are classic considerations in a serious unexplained acidosis. These substances may generate metabolites that elevate the gap and can require urgent attention. A high result should therefore prompt a careful review of history, medication exposure, symptoms, and other blood tests.
Frequent Causes of a reduced anion gap
A low anion gap is less common and often warrants a closer look rather than being ignored. The most common reason is hypoalbuminemia. Since albumin contributes significantly to the unmeasured anion pool, a reduced albumin level can lower the gap even when other chemistry values look normal.
Laboratory error is another important possibility. Because the anion gap is derived from other values, any mistake in sodium, chloride, or bicarbonate can alter the final answer. Repeating the blood test may be advisable when the result does not fit the clinical picture.
Paraproteinemia, such as in certain plasma cell disorders, can also decrease the gap. In these conditions, abnormal proteins may interfere differently than expected and change the balance of measured and unmeasured ions. This is one reason the anion gap is useful as a screening clue rather than a single diagnosis.
In some cases, a low gap reflects a blend of factors, including low albumin, changes in serum electrolytes, or atypical blood chemistry patterns. The key is to evaluate the result in the broader context of the patient’s symptoms and full clinical interpretation.
Drawbacks of the Calculator and Clinical Context
An anion gap calculator is helpful, but it has limitations. It uses measured values from blood tests and cannot account for all forms of acid-base change. A normal result does not rule out all acid-base disorders, and an abnormal result does not reveal the exact cause on its own.
Another limitation is that different laboratories may use different analytic methods, which can alter the reference range. That means the same patient may seem to have a slightly different result depending on the instrument, reporting style, or whether the formula includes potassium. The calculator should therefore be used as a screening and interpretation aid, not as a final diagnostic endpoint.
Clinical context matters just as much as the number itself. Symptoms, physical exam findings, medication use, kidney function, and the rest of the electrolyte panel all shape interpretation. For example, a modestly elevated gap in a patient with suspected metabolic acidosis may be more significant than the same value in someone with no symptoms.
Good clinical interpretation also depends on whether the result is being compared with a baseline value. A change from the patient’s usual pattern may be significant even if the number still falls within a typical range. For this reason, the calculator is best viewed as one part of a broader diagnostic toolset.
FAQs About the Anion Gap Calculator
What is an anion gap calculator with potassium included?
An anion gap calculator with potassium included is a tool that estimates the gap using sodium, chloride, bicarbonate, and potassium. It uses a modified anion gap formula rather than the traditional one. This version can be beneficial when you want a more complete accounting of measured electrolytes.
Why might potassium be included in the anion gap formula?
Potassium may be added because it is a measured cation and helps determine the overall ion balance. Adding it creates a modified anion gap that may be relevant in some educational settings. However, most routine clinical references still use the traditional anion gap, so the formula must match the reference range being used.
What would be the normal anion gap range when potassium is included?
The normal range is increased when potassium is included because the formula adds one more cation. The exact range depends on the laboratory and the calculator method. Always compare the result with the reference range provided for the specific formula, not with a standard range from a calculator that excludes potassium.
What does a high anion gap indicate?
A high anion gap often indicates extra acids in the blood, which can occur in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols. It usually points toward some form of metabolic acidosis. The exact cause depends on the rest of the labs and the overall clinical picture.
Could a normal anion gap still mean there is a medical problem?
Yes. A normal result does not exclude a medical issue, because not every acid-base disorder changes the gap. Some conditions cause a non-gap metabolic acidosis, while others may be present despite a normal calculation. The result should always be interpreted alongside symptoms, other blood chemistry values, and the full electrolyte panel.