What Is the Anion Gap?
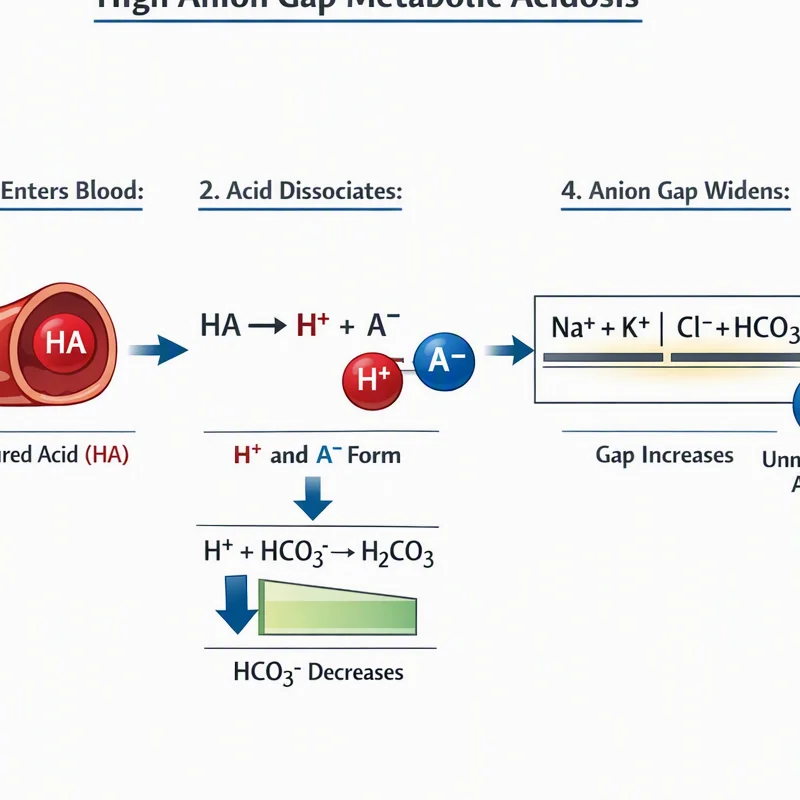
The anion gap is a computed value used to assist evaluate acid-base equilibrium and electrolyte disturbance. It comes from routine blood chemistry and compares the main measured cations and anions in the blood, especially sodium and chloride, along with serum bicarbonate. Because not every charged particle is directly measured, the anion gap helps identify the existence of unmeasured anions and provides a useful diagnostic clue in metabolic acidosis.
In practical terms, the anion gap represents the difference between measured electrolytes in a serum chemistry panel. A typical anion gap formula uses sodium, chloride, and bicarbonate to estimate whether there are extra acids in the blood or whether bicarbonate has been lost. Clinicians use this result as part of the broader interpretation of a laboratory result, not as a standalone answer.
The value is most informative when viewed in clinical context. A normal or elevated number does not by itself tell the whole story about severity, because the body may be in an acidotic state for different reasons. That is why the anion gap is often paired with other tests, including arterial blood gas testing, to understand the full metabolic disturbance.
How an Anion Gap Calculator Works
An anion gap calculator simplifies the computation from blood values, usually sodium, chloride, and serum bicarbonate. This makes it easier to quickly estimate whether the gap is within the expected reference range or whether it suggests high anion gap acidosis. The calculator is especially helpful when reviewing multiple lab results or tracking changes over time.
Many modern calculators also include albumin correction. Albumin is a negatively charged protein, so lower albumin can make the measured gap appear deceptively normal. An albumin-corrected anion gap refines the result to better reflect true acid burden. This corrected gap can reveal hidden acid retention even when the uncorrected number seems unremarkable.
Because albumin changes the expected baseline, a normal value on the uncorrected calculation may not truly be normal. In other words, the corrected gap is often more informative than the raw number, especially when the blood chemistry suggests an acidotic state but the anion gap appears borderline. A good calculator supports better interpretation by considering these physiologic shifts.
Using an anion gap calculator does not replace judgment. It is a calculated value that must be considered alongside pH, base excess, serum electrolytes, and the overall pattern of the metabolic disturbance. The calculator is a tool, but the diagnosis comes from integrating the numbers with the patient’s condition.
Can Profound Acidosis Have a Unchanged Anion Gap?
Indeed. Severe acidosis can certainly occur with a unchanged anion gap. Here is the important point many people miss. A normal corrected anion gap calculator gap does not rule out significant metabolic acidosis; it only implies that the acid-base problem is not being driven by a large accumulation of unmeasured anions. In normal anion gap acidosis, the main problem is usually depletion of bicarbonate or a related shift in chloride.
This pattern is also called hyperchloremic acidosis because chloride rises to maintain electrical neutrality as bicarbonate declines. The result is marked acidemia in some cases, yet the anion gap stays within the expected range. The body is still acidic, but the chemistry pattern is different from high anion gap acidosis.
In severe cases, the serum bicarbonate may be very low, and the pH can be substantially reduced. The anion gap remains normal because the fall in bicarbonate is balanced by a rise in chloride. This is why a normal gap should never be interpreted as “no acidosis.” It simply points the clinician toward bicarbonate loss or chloride retention rather than excess unmeasured acids.
Knowing this distinction is important in differential diagnosis. A patient with a normal anion gap and low bicarbonate may still be quite ill. The severity of the acidotic state is reflected more directly by pH and base deficit than by the gap itself.
Frequent Causes of Normal Gap Metabolic Acidosis
A number of conditions can produce normal anion gap acidosis. A very common cause is diarrhea, which causes direct bicarbonate loss from the gastrointestinal tract. When bicarbonate is removed, chloride often increases to preserve electroneutrality, creating a normal gap pattern.
Renal tubular acidosis is a further major cause. In these disorders, the kidneys fail to appropriately manage hydrogen ions or bicarbonate, causing persistent metabolic acidosis. Depending on the subtype, the blood may show low serum bicarbonate with normal or increased chloride. Even so, the anion gap can remain normal even when the acidosis is clinically significant.
Other common mechanisms involve either inadequate bicarbonate regeneration or excessive chloride exposure. Large-volume saline administration, for example, can contribute to chloride retention and a hyperchloremic pattern. This is not always dramatic on the surface, but it can substantially affect acid-base balance and blood chemistry.
These mechanisms share a similar laboratory signature:
- Reduced serum bicarbonate Relatively high chloride Unremarkable or near-normal anion gap Evidence of metabolic acidosis on blood gas testing
The pattern supports a targeted diagnostic approach. Instead of searching first for lactate or ketoacidosis, clinicians should consider bicarbonate loss, chloride retention, and kidney-related causes when the gap is normal.
When a Regular Anion Gap Can Be Deceptive
A regular anion gap can be deceptive when additional issues mask the real acid burden. One major issue is albumin. Because albumin is a major unmeasured anion, reduced albumin can depress the measured gap. Without albumin correction, a patient with serious acidemia may look to have a normal value even though the corrected gap is actually increased.
This matters particularly in a mixed acid-base disorder. For instance, a patient may have both lactic acidosis and bicarbonate loss, or ketoacidosis plus concurrent hyperchloremic acidosis. One mechanism may raise the gap while another brings it back toward normal. In that setting, the measured result can obscure the presence of high anion gap acidosis.
Lactate and ketoacidosis are well-known causes of elevated gaps, but they may not always present in a simple, isolated pattern. If the body has already shed bicarbonate or received large amounts of chloride-containing fluid, the gap may look normal despite a serious metabolic problem. That is why the calculated number must be read with the full clinical picture.
In short, a normal gap can represent:
- Actual normal anion gap acidosis A mixed disorder that balances out the numbers Hypoalbuminemia concealing an elevated corrected gap A timing issue, where lab values vary as the condition evolves
So the normal result is not the final step of the workup. It is a diagnostic clue that should be weighed against the patient’s symptoms, serum electrolytes, and other studies.
How to Read Findings in Patient Context
Interpreting the anion gap properly requires integrating several clinical clues. The arterial blood gas supplies key information about pH and ventilation, while the serum chemistry panel reveals the underlying electrolyte pattern. In combination, they indicate whether the patient has acidemia, the extent of the problem, and whether compensation is present.
The pH tells you whether the blood is acidotic or alkalemic. The base excess helps measure the degree of metabolic abnormality, while serum bicarbonate shows the buffering status directly. If pH is low and bicarbonate is low, the patient is definitely in a metabolic acidosis, even if the anion gap is normal.
Clinical context matters because the same laboratory result can mean different findings depending on the situation. A normal gap in a patient with diarrhea may fit bicarbonate loss. In someone with diabetic symptoms, the same result may suggest a mixed acid-base disorder or a corrected gap that should be reviewed carefully. The interpretation is never just arithmetic; it is clinical reasoning.
Key considerations to consider include:
- Review the albumin level and evaluate the corrected gap Inspect the serum chemistry panel for chloride and bicarbonate trends Confirm the acid-base status with arterial blood gas results Check for evidence of compensation or a mixed disorder Rely on pH and base excess to assess severity, not only the anion gap
The best approach is to treat the anion gap as one part of a broader evaluation. It supports the differential diagnosis, but it does not substitute for a full acid-base assessment.
FAQ
Can severe acidosis happen with a normal anion gap?
Indeed, it can. Severe acidosis can occur with a normal anion gap, especially in normal anion gap acidosis. This commonly occurs when bicarbonate is lost or when chloride increases to compensate for the drop in bicarbonate. The patient can still be significantly acidotic even if the gap is within the normal range.
What conditions cause a normal anion gap metabolic acidosis?
Typical causes include diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. Retained chloride can likewise cause this pattern. These conditions typically create hyperchloremic acidosis with a normal or near-normal anion gap.
How does albumin affect the anion gap interpretation?
Because albumin is a major unmeasured anion, low albumin can cause the anion gap to seem falsely normal. Albumin correction helps uncover the true corrected gap. This is especially important when the clinical picture suggests more severe metabolic acidosis than the initial number implies.
Can ketoacidosis or lactic acidosis present with a normal anion gap?
Yes, they may. Although ketoacidosis and elevated lactate typically cause high anion gap acidosis, the gap may look normal in a mixed acid-base disorder or when hypoalbuminemia is present. Prior bicarbonate loss or chloride loading can also mask the expected elevation.
How should an anion gap calculator be combined with blood gas results?
An Anion Gap Calculator should be used together with arterial blood gas results, not in place of them. The calculator helps determine whether the pattern matches normal or high anion gap acidosis, while the blood gas displays pH, base excess, and overall severity. Used together, they give a more complete interpretation of the acid-base disturbance.