An anion gap calculator is a practical diagnostic tool designed to help interpret a blood chemistry panel or electrolyte panel. It combines serum sodium, chloride, and bicarbonate to calculate a calculated value that helps with clinical interpretation of acid-base balance. While the number itself is simple, the meaning behind it depends on the full lab result, including albumin, the overall electrolytes, and the patient’s assessment.
This guide shows how the anion gap works, how the anion gap formula relies on sodium and related measurements, and why the result can point toward a certain metabolic disturbance such as metabolic acidosis or high anion gap metabolic acidosis. It also covers albumin correction, corrected anion gap use, reference range interpretation, and key diagnostic limitations.
How this Anion Gap Shows
The anion gap estimates the difference between measured positive and negative charges in the blood. In everyday terms, it may indicate whether there are extra unmeasured ions in the bloodstream that may affect the body’s acid-base balance. Because the body keeps electrolytes in a narrow range, even small shifts in serum sodium, chloride, and bicarbonate can provide useful clues.
Most clinicians rely on the anion gap as part of a broader serum chemistry review. It is not a standalone diagnosis. Instead, it is one piece of evidence that can support the interpretation of a metabolic acidosis workup, especially when a patient has complaints or other abnormal lab findings.
The idea behind the anion gap is that sodium is usually the main measured positive ion, while chloride and bicarbonate are two of the main measured negative ions. The gap reflects what is not directly measured. That is why the result can be useful when looking for hidden causes of a metabolic disturbance.
Anion Gap Formula
The usual anion gap formula is easy to use:
Anion gap = sodium - (chloride + bicarbonate)
A few calculators include potassium, but most current references leave it out for clarity. The essential inputs are the sodium concentration, chloride level, and bicarbonate level. After the values are entered into an anion gap calculator, the tool provides a fast measurement that can be compared with the expected reference range.
For instance, if the sodium is 140, the chloride is 102, and the bicarbonate is 24, the calculation is:
140 - (102 + 24) = 14
That calculated value may fit within many commonly used normal limits, depending on the lab. As ranges vary, the result should always be interpreted alongside the specific laboratory’s reported range and the overall clinical interpretation.
In use, the anion gap calculator is useful because it streamlines the interpretation of a routine blood chemistry panel. The calculator does not replace judgment; it structures the data so patterns become easier to identify.
How Serum Sodium Influences the Calculation
Serum sodium is key to the formula because it grounds the formula. Since sodium is the most abundant measured cation in the blood, any change in its concentration can change the anion gap result. That does not mean sodium directly causes the acid-base problem, but it can affect the final number and how the electrolyte balance is understood.
If sodium is low or high, the relationship between sodium, chloride, and bicarbonate shifts. The resulting lab result may still be informative, but the context matters. For example, a low sodium value can make the calculated gap less clear to interpret if the rest of the electrolytes are altered at the same time.
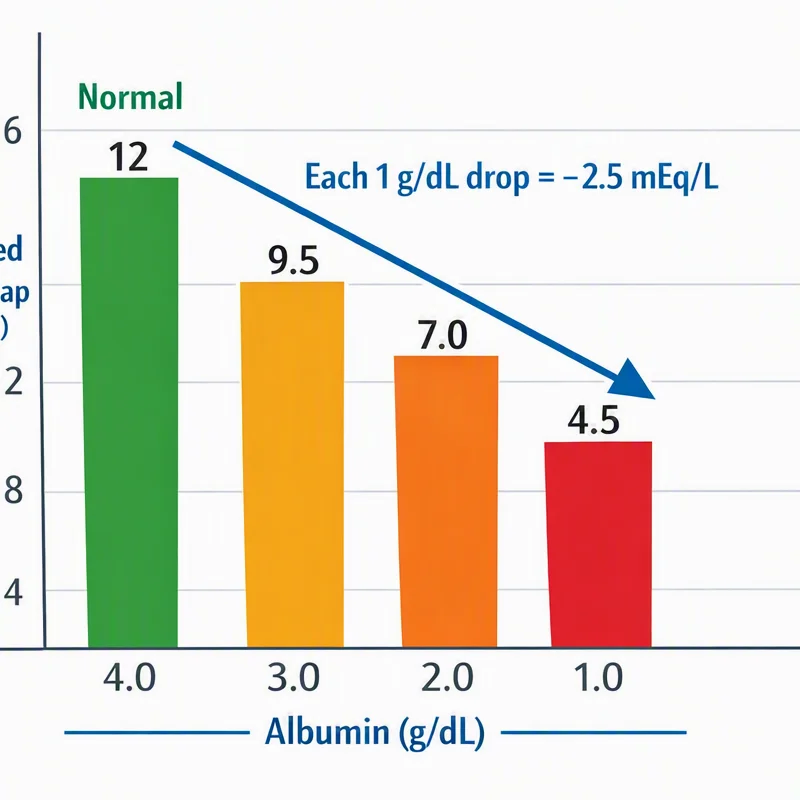
Albumin also matters here. Because albumin is a negatively charged protein, lower albumin can make the anion gap appear lower than it truly is. This is why albumin correction is sometimes used to estimate a corrected anion gap. In a patient with hypoalbuminemia, the unadjusted number may underestimate the degree of underlying acid-base abnormality.
The corrected result is not a separate diagnosis. Rather, it is a correction factor applied to improve interpretation. This is especially important when the goal is to anion gap clinical significance evaluate a hidden cause of metabolic acidosis or to detect a subtle change in serum chemistry.
Typical, Elevated, and Low Anion Gap Results
The reference range for the anion gap depends on the lab technique and whether potassium is included. That said, the result is usually categorized as normal anion gap, increased anion gap, or low anion gap.
A anion gap within normal limits often suggests that the measured electrolytes are balanced in a standard way, though it does not automatically mean there is no problem. A elevated anion gap metabolic acidosis usually points to the presence of extra acids or unmeasured charged particles in the blood. A decreased anion gap is less common and may reflect low albumin, lab variation, or other issues that affect the measurement.
It is important to remember that “normal” is lab-specific. A result that seems borderline in one setting may be acceptable in another. This is why a full clinical review should consider the specific blood chemistry panel, the patient’s symptoms, and the broader pH balance.
In practical terms:
- Normal gap: may be seen when the electrolyte pattern does not suggest excess unmeasured acids. Elevated anion gap metabolic acidosis: suggests extra acid accumulation or another process increasing the gap. Low anion gap: may indicate hypoalbuminemia, lab variation, or a less common abnormality.
Frequent Causes of Atypical Anion Gap Values
Various conditions may alter the anion gap and indicate a specific cause of metabolic acidosis. The most frequent causes are lactic acidosis, ketoacidosis, renal failure, and hypoalbuminemia.
Lactic acidosis happens when lactate builds up faster than the body can clear it. This may be seen with low oxygen delivery, severe illness, or other metabolic stress. Since lactate is an unmeasured anion, the gap may rise.
Ketoacidosis can develop when ketones accumulate, for example in uncontrolled diabetes or prolonged fasting. These ketones add to the amount of unmeasured acids, often leading to high anion gap metabolic acidosis.
Renal failure can reduce the body’s ability to eliminate acids. As acid retention increases, the anion gap may become elevated. This finding can be particularly useful when paired with the rest of the electrolytes and kidney-related markers on the blood chemistry panel.
Hypoalbuminemia, on the other hand, may lower the measured gap. Because albumin contributes to the negative charge balance, low albumin can make the result appear deceptively normal or reduced. This is where albumin correction and the corrected anion gap become useful in clinical interpretation.
There may be other causes as well, but these four are among the most frequently considered when reviewing an elevated or reduced anion gap.
Stepwise: Interpreting Calculator Output
Evaluating an anion gap calculator output is not just typing in numbers and seeing a result. A thorough process improves assessment and helps avoid mistakes.
Step 1: Review the electrolyte values. Check the serum sodium, chloride, and bicarbonate values from the electrolyte panel or blood chemistry panel. Verify the units and sample are correct.
Step 2: Calculate the anion gap. Apply the anion gap formula to obtain the calculated value. Assess it with the lab’s reference range rather than assuming a universal cutoff.
Step 3: Consider albumin. If albumin is low, apply albumin correction to estimate the corrected anion gap. This may show a hidden elevation that would otherwise be missed.
Step 4: Match the pattern to the clinical picture. Watch for signs of acid-base disorder, dehydration, kidney dysfunction, or other causes of metabolic disturbance. The result should align with the patient’s symptoms and other lab findings.
Step 5: Form a clinical interpretation. A single number is not enough. Integrate the anion gap with the rest of the serum chemistry, the history, and the physical findings to make a reasonable conclusion.
A useful anion gap result is one that supports the full story, not one that exists alone.
Drawbacks of Anion Gap Calculation
Even though the anion gap is valuable, it has clear limits in diagnosis. The calculation depends on measurement methods, lab handling, and the situation in which the result is used.
One limitation is albumin adjustment. When albumin is not considered, the result may fool the interpreter. This is especially relevant in patients with hypoalbuminemia, where the measured gap can be incorrectly low or normal.
Another limitation is test variation. Different analyzers and reporting methods can produce slightly different reference intervals. A number that seems abnormal in one lab may fit inside a different lab’s expected interval.
The calculation also does not directly identify the cause of the problem. It simply points to the possible presence of unmeasured substances or a shifted electrolyte pattern. Additional testing and context are needed to confirm the cause, whether that is lactic acidosis, ketotic acidosis, kidney failure, or something else.
Finally, the anion gap should not be used as a substitute for direct clinical care. It is best viewed as one part of a broader diagnostic approach to pH balance and clinical assessment.
When to Seek Medical Review
Abnormal anion gap findings should be reviewed by a healthcare provider, especially when they occur with concerning complaints. Signs such as severe weakness, rapid breathing, confusion, vomiting, chest discomfort, or worsening illness may signal a serious metabolic acid buildup or another urgent condition.
An elevated or reduced result does not always mean emergency care is needed, but it does https://ameblo.jp/anion-gap-formula852/entry-12977185268.html mean the test should be understood in context. If a chemistry panel shows a concerning pattern, prompt timely assessment may be appropriate to assess the underlying cause.
People with diabetes, kidney disease, infection, dehydration, or known electrolyte imbalances may need careful evaluation if the anion gap is outside the normal range. The same is true if the result varies greatly from prior testing or doesn’t fit the patient’s clinical status.
When in doubt, check in with a clinician who can read the result alongside signs, exam findings, and other laboratory data.
FAQs About Anion Gap and Serum Sodium
What is an anion gap calculator with serum sodium used for?
An anion gap calculator with serum sodium is used to derive the anion gap from common electrolytes on a blood chemistry panel. It helps with clinical interpretation of acid-base problems, especially when evaluating metabolic acidosis or checking for a hidden metabolic issue.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
Use the anion gap calculation: sodium - (chloride + bicarbonate). The serum sodium level, chloride level, and bicarbonate level are entered into the calculator to produce the calculated value.
Why does serum sodium matter in an anion gap calculation?
Serum sodium matters because it is the main measured cation in the formula. Changes in sodium can affect the final number and the way the acid-base status is interpreted. Sodium also helps anchor the relationship between the measured electrolytes and the overall charge balance.
What does a high anion gap mean?
A elevated anion gap often suggests extra acids or unmeasured ions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. It can be a clue to high anion gap metabolic acidosis, but the full clinical picture is needed for interpretation.
Can a standard anion gap also indicate a health issue?
Certainly. A normal anion gap doesn't rule out a disease or an acid base problem. Some cases may not alter the gap much, and laboratory result review must take into account symptoms, other labs, and the patient’s total condition. Medical interpretation should always go beyond the number alone.