What’s the Serum Anion Gap?
The serum anion gap is a derived value used in serum chemistry to help evaluate acid-base disorders, especially metabolic acidosis. It comes from a standard electrolyte panel and captures the balance between major measured serum electrolytes such as sodium, chloride, and bicarbonate. Because blood contains other positively and negatively charged particles that are not directly measured, the anion gap helps estimate the presence of unmeasured anions.
In simple terms, the serum anion gap is a sign of anion concentration differences in the blood. A higher-than-expected value usually suggests that acids or acid byproducts are accumulating. That is why the serum anion gap is a valuable diagnostic tool during laboratory assessment of patients with unexplained acidosis, shock, poisoning, or kidney dysfunction.
The classic formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
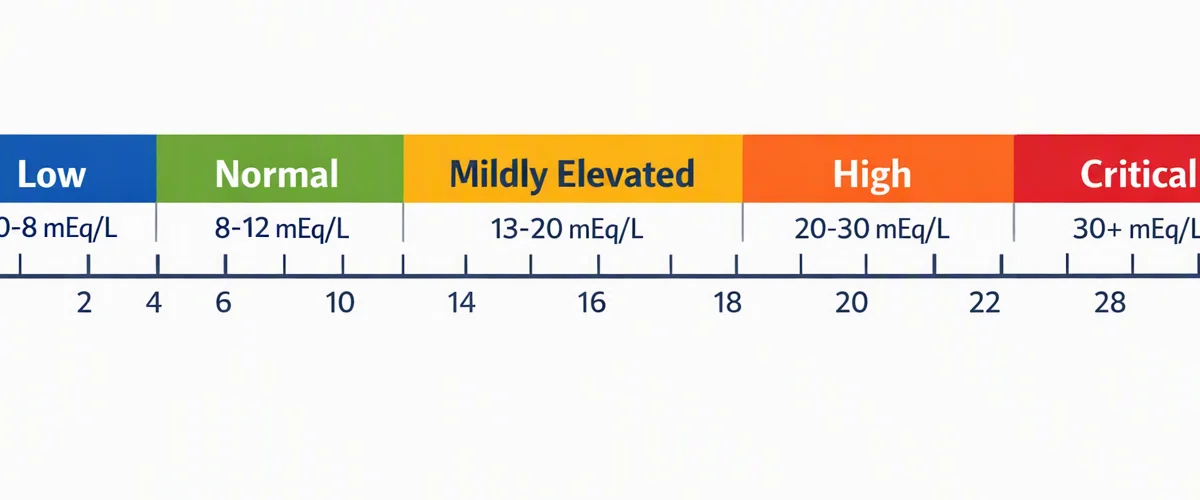
Some clinicians also include potassium in the calculation, but the most commonly used version excludes it because potassium contributes relatively little to the result. A normal serum anion gap often falls within a small range, but the exact normal range depends on the laboratory method used and whether potassium is included.
The serum anion gap is closely tied to acid-base balance and electrolyte balance. When bicarbonate drops because it is being consumed by acids, the gap can rise if the lost bicarbonate is replaced by unmeasured acids. This makes the serum anion gap especially helpful in identifying the underlying type of metabolic acidosis.
Understanding the Urine Anion Gap
The urinary anion gap is a different calculation based on urine electrolytes. Instead of assessing the blood directly, it helps gauge how well the kidneys are responding to acid loads by evaluating urinary acid excretion indirectly. It is usually calculated from urine sodium, potassium in urine, and chloride in urine.
The standard formula is:
Urine anion gap = Urine sodium + Urine potassium − Urine chloride
This number is commonly used as a surrogate marker for ammonium excretion, which is a primary way the kidneys eliminate acid. When urine chloride is greater in relation to urine sodium and potassium, the urine anion gap often becomes less than zero, pointing to greater ammonium excretion. When the gap is above zero, it may suggest impaired renal acid excretion.
Unlike the serum anion gap, the urine anion gap does not chiefly focus on identifying unmeasured anions in blood. Instead of that, it is a way for evaluating renal handling of acid and evaluating whether the kidneys are appropriately responding in the context of non-anion gap metabolic acidosis.
The UAG can be especially helpful useful when clinicians need to differentiate whether a metabolic acidosis is due to a renal problem or to extrarenal losses such as gastrointestinal bicarbonate loss. In this context, the urine anion gap offers indirect insight into ammonium production, kidney function, and overall acid excretion.
Serum Anion Gap vs Urine Anion Gap: Key Differences
While both tests use the term “anion gap,” they serve different medical questions. The serum anion gap centers on the blood and is most useful for evaluating metabolic acidosis caused by accumulated acids. The urine anion gap centers on the kidneys and is most useful for evaluating whether the kidneys are eliminating acid appropriately.
The key difference is the system being assessed. The serum anion gap shows electrolyte balance in the bloodstream and helps identify excess acid or loss of bicarbonate substituted by other anions. The urine anion gap shows urinary electrolytes and helps approximate renal ammonium excretion, which is central to the kidney’s response to acid retention.
Clinically, the serum anion gap is frequently the first test used when someone has acid-base abnormalities. If the serum gap is elevated, clinicians evaluate causes such as lactic acidosis, ketoacidosis, or toxic alcohols. If the serum anion gap is not elevated but acidosis is still present, the problem may be a non-anion gap metabolic acidosis, and the urine anion gap may help show whether the issue is renal or extrarenal.
This is a practical way to think about the difference:
- Serum anion gap: identifies abnormal acids in blood and assists acid-base interpretation. Urine anion gap: estimates kidney acid excretion and helps assess ammonium excretion. Serum test: relies on sodium, chloride, and bicarbonate from the electrolyte panel. Urine test: relies on urine sodium, urine potassium, and urine chloride.
Both are helpful in clinical interpretation, but they are used for distinct parts of the differential diagnosis. The serum anion gap asks, “What acids are present in the blood?” The urine anion gap asks, “How is the kidney responding?”
How the Anion Gap Calculator Works
An anion gap calculator streamlines the simple calculations used in clinical practice and can minimize mistakes during rapid evaluation. The calculator typically uses the anion gap formula based on serum sodium, chloride, and bicarbonate. Some versions also include potassium-inclusive calculations and present a corrected anion gap when albumin is low.
Why does albumin matter? Albumin is a key unmeasured anion in the blood. When albumin decreases, the serum anion gap can appear falsely low or normal even if significant acid is present. That is why a corrected value is often more informative than the raw number alone.
A common correction approach applies a set amount to the measured anion gap for each drop in albumin below normal. The exact adjustment can vary by institution, but the concept is the same: low albumin can mask a real gap. A corrected anion gap strengthens acid-base interpretation and helps prevent missed diagnoses.
Using the calculator effectively requires the right inputs from the electrolyte panel. For serum calculations, that means sodium, chloride, bicarbonate, and sometimes albumin. For urine calculations, it means urine sodium, urine potassium, and urine chloride. Because results can vary by lab reference standards, the normal range should always be interpreted alongside the patient’s clinical picture and the local laboratory method.
The most important limitation is that a calculator provides a number, not a diagnosis. The value must be interpreted in context with symptoms, blood gas data, kidney function, and other laboratory values. Used correctly, an anion gap calculator is a practical diagnostic tool for day-to-day laboratory assessment.
When to Check Serum Anion Gap
The serum anion gap is especially helpful when there is concern for high anion gap metabolic acidosis. This is the usual scenario in which acids accumulate in the blood and consume bicarbonate, leaving behind excess unmeasured anions. Common causes include lactic acidosis, ketoacidosis, and toxic alcohols.
In lactic acidosis, tissue hypoperfusion, sepsis, seizures, or severe illness can increase lactate production and tax normal buffering systems. In ketoacidosis, the body produces ketone acids in conditions such as diabetes, starvation, or alcohol-related illness. In toxic alcohols exposure, metabolites such as formate or glycolate can cause a marked increase in the serum anion gap.
The serum anion gap is also valuable when the cause of acidosis is not obvious. A normal bicarbonate level does not always rule out acid-base problems, especially when mixed disorders are present. A rising gap may be an early sign of worsening illness before other changes become obvious. In this sense, the serum anion gap provides a quick window into acid-base disorders and the balance between measured and unmeasured ions.
Another common use is monitoring the anion gap over time. If treatment is effective, the gap should often decrease as the underlying cause is addressed. That can help clinicians follow response during ongoing management of acidosis, shock, intoxication, or renal impairment.
When to Employ Urine Anion Gap
The urine anion gap is especially useful in evaluating non-anion gap metabolic acidosis, particularly when the question is whether the kidneys are functioning appropriately. This is where renal tubular acidosis becomes a major consideration. In renal tubular acidosis, the kidneys fail to acidify urine normally, leading to poor acid excretion despite ongoing acid load.
Because the urine anion gap estimates ammonium excretion, it can help distinguish renal from nonrenal causes of non-anion gap metabolic acidosis. If ammonium excretion is high, the kidneys are responding appropriately, which argues against a primary kidney acidification problem. If ammonium excretion is low, the problem may be related to kidney disease or tubular dysfunction.
This test is most useful when gastrointestinal bicarbonate loss is possible. For example, in diarrhea, the body loses bicarbonate from the gut, causing non-anion gap metabolic acidosis. In that scenario, the kidneys should increase ammonium production and urine chloride excretion, often producing a negative urine anion gap. That pattern suggests intact renal anion gap clinical significance compensation.
In contrast, a positive urine anion gap in a patient with acidosis may suggest the kidneys are not excreting acid effectively. That finding can indicate a diagnosis of renal tubular dysfunction, chronic interstitial damage, or other forms of kidney disease. The urine anion gap therefore plays a key role in assessing renal handling of acid and the body’s ability to maintain acid-base balance.
How to Interpret Results in Clinical Practice
Clinical reading starts with recognizing whether the problem is primarily in blood chemistry, urine chemistry, or both. The serum anion gap and urine anion gap are not equivalent; each contributes different information to the differential diagnosis. Correct interpretation requires the full picture, including symptoms, blood gas data, and the broader electrolyte disorders pattern.
A elevated serum anion gap usually suggests a build-up of unaccounted-for acids. That may suggest diagnoses like lactic acidosis, ketoacidosis, toxic alcohols, or advanced renal failure. A normal serum anion gap with acidosis suggests a different path, often non-anion gap metabolic acidosis, where bicarbonate is lost and replaced by chloride.
The urine anion gap offers another layer of interpretation. A favorable urine anion gap often implies effective ammonium excretion, which is common in diarrhea-related acidosis. A high urine anion gap can indicate impaired renal acid excretion, which may be seen in renal tubular acidosis or other forms of kidney disease.
Lab results should never be read in isolation. Albumin, potassium, sodium, bicarbonate, chloride, creatinine, and blood gas measurements all influence interpretation. A patient with hypoalbuminemia may have a deceptively normal serum anion gap. A patient with severe illness may have mixed Hop over to this website acid-base disorders that obscure the expected pattern. This is why the anion gap should be viewed as one part of a broader laboratory assessment rather than a stand-alone answer.
Typical Reasons of Abnormal Anion Gap Values
Several conditions can affect the serum anion gap, the urine anion gap, or the two. One of the most common causes of a falsely low or apparently normal serum anion gap is hypoalbuminemia. Because albumin is a key unmeasured anion, low levels decrease the apparent gap and can hide a clinically important metabolic disturbance.
Chronic kidney disease can also influence results. In advanced disease, acid excretion may decline, and the serum anion gap may rise as retained acids accumulate. At the same time, kidney dysfunction can reduce ammonium production and lead to abnormal urine anion gap findings. This is why kidney function is fundamental to both serum and urine interpretation.
Diarrhea is a classic cause of hyperchloremic metabolic acidosis because it causes bicarbonate loss from the gut. In that setting, serum bicarbonate falls, but the serum anion gap may persist normal unless another acid load is present. The urine anion gap may become negative if the kidneys respond properly by increasing ammonium excretion.
Sepsis often causes elevated lactate and therefore a high serum anion gap. In severe cases, blood flow abnormalities, organ dysfunction, and altered buffering systems can create complex acid-base patterns. Sepsis can therefore produce high anion gap metabolic acidosis, mixed disorders, or both, making serial laboratory assessment essential.
Other contributors to abnormal values include medication effects, dehydration, vomiting, urinary losses, and changes in potassium or chloride handling. Because acid-base disturbances often overlap, the clinician should use the serum anion gap and urine anion gap as part of a systematic approach rather than as isolated numbers.
Frequently Asked Questions
What is the difference between serum anion gap and urine anion gap?
The serum anion gap measures the difference between major measured blood electrolytes, mainly sodium, chloride, and bicarbonate, to help detect unmeasured anions and evaluate acid-base disorders. The urine anion gap uses urine sodium, urine potassium, and urine chloride to estimate ammonium excretion and assess how well the kidneys are responding to acidosis.
How do you compute serum anion gap with an Anion Gap Calculator?
An anion gap calculator usually uses the formula sodium less the sum of chloride and bicarbonate. Some calculators also incorporate potassium or give a corrected anion gap when albumin is low. You provide the laboratory values, and the tool performs the calculation to aid clinical interpretation.
When is urine anion gap more useful than serum anion gap?
The urine anion gap is more valuable when evaluating non-anion gap metabolic acidosis, especially if the question is whether the kidneys are excreting acid properly. It is particularly important in suspected renal tubular acidosis or when trying to distinguish renal causes from bicarbonate loss due to diarrhea.
What does a high serum anion gap mean?
A high serum anion gap usually indicates there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, and toxic alcohols. It can also occur with advanced chronic kidney disease or other conditions that lead to acid retention.
Can a normal anion gap still indicate a serious acid-base disorder?
Yes. A normal anion gap does not rule out a serious problem. It may reflect non-anion gap metabolic acidosis, mixed acid-base disorders, or a masked disturbance from hypoalbuminemia. That is why the full clinical context, including albumin, bicarbonate, potassium, and other laboratory values, is necessary for accurate clinical interpretation.